


I don’t know about you, but I find AI chatbots increasingly enticing.
I wouldn’t rely on them for wisdom, psychological advice, romantic fulfillment, or the content of these newsletters. It’s their knowledge that attracts me.
This is the siren song of AI chatbots.
In The Odyssey, the sirens promise that whoever hears their song will know “everything that happens on the fertile earth”. Nowadays, the chatbots make a similar promise, though their song can be dangerous too.
Why? Simply put, AI sometimes misrepresents its sources. Sometimes the sources themselves are misleading and AI doesn’t realize it.
I encountered both perils this week after hearing about a new statement from the American Heart Association. On Tuesday, when I googled this statement, AI Overview immediately offered the following:

Sorry, no. The AHA does not advise adults to consume caffeine. Not in the new statement, not anywhere.
In this newsletter I want to discuss what the new AHA statement actually does say.
My interests are practical: How much caffeine can a person safely consume? What are the potential health benefits? How much concrete guidance does the AHA statement offer?
I think this statement merits a close look. Roughly 90% of American adults use caffeine, the science on its health impacts is evolving, and the new statement has already been covered by high-circulation outlets like ABC News and the Wall Street Journal, which are in turn “read” by the most popular AI chatbots. (51% of Americans use these bots, according to a June survey, most commonly for seeking out information.)

A new scientific statement
The AHA statement was coordinated by lead author Dr. Gregory Marcus (UC San Francisco) and published in the journal Circulation on July 20th.
If, like me, you drink caffeine in moderation, this document may seem like great news. Here’s the bottom line:
“[M]oderate caffeine or coffee consumption (up to 400 mg/d caffeine or ≈3–5 cups of coffee at 8 oz per cup) is safe for most adults and is associated with lower risk of cardiovascular disease, including coronary heart disease, stroke, heart failure, and AF [atrial fibrillation], as well as hypertension and type 2 diabetes.”
That’s impressive. Unfortunately, the AHA statement is also plagued by inconsistencies, impracticality, and bias.
To be fair, it’s not easy to synthesize evidence on a complex topic. I’m grateful to anyone who makes the effort.
I interviewed two cardiologists for this newsletter, including James Stein, the Robert Turell Professor of Cardiovascular Research at University of Wisconsin and one of my favorite Substack authors.
In an email to me this week, Dr. Stein noted that “it’s a service to write these [statements] when the data are incomplete, and to provide expert guidance, but then the guidance needs to be clear and honest about its limitations and, importantly, to avoid moralizing.”
I agree. And I don’t think the AHA statement lives up to these standards.
1. Inconsistencies.
Here I’ll share just one example involving hypertension (i.e., high blood pressure), a key risk factor for cardiovascular disease.
The AHA statement contains three contradictory claims about caffeine-hypertension associations:
Claim 1: “[M]oderate caffeine or coffee consumption (up to 400 mg/d caffeine or ≈3–5 cups of coffee at 8 oz per cup) is safe for most adults and is associated with lower risk of...hypertension.”
In other words, drinking up to 3 to 5 cups of coffee per day reduces risk.
Claim 2: “Prospective cohort studies with long-term follow-up have [demonstrated] an increased risk [of hypertension] with intake of 1 to 3 cups/d but a trend toward a decreased risk with higher consumption.”
In other words, drinking up to 3 cups of coffee per day increases risk. Only higher intake may reduce risk. This mostly contradicts Claim 1.
Claim 3: “The long-term effects of habitual caffeine consumption on blood pressure remain unclear and are likely minimal, although the risk may increase with high intake....”
Here the claim is that the effects on risk, though probably minimal, are unclear, though higher intake may increase risk.
This is so confusing! Does moderate caffeine intake reduce the risk of hypertension (Claim 1), increase risk (Claim 2), or do we just not know for sure (Claim 3)? Does higher intake decrease risk (Claim 2) or increase it (Claim 3)?
It’s hard to defer to the experts if they don’t get their story straight.
I reached out to Dr. Marcus, the lead author, in hopes of clarification. His reply seemed most closely aligned with the agnosticism of Claim 3:
“The big picture lesson from the data is that caffeine, or commonly consumed caffeinated products, apparently do not simply always increase blood pressure. Caffeine has other effects, such as some possible vasodilation as well as clear diuretic effects that may have blood pressure-lowering properties. We also know that tolerance can develop when caffeine is consumed....”
In effect, what Dr. Marcus is saying is that in the short run, caffeine affects our bodies in many ways. The blocking of adenosine receptors that increases alertness causes blood vessels to constrict, thereby raising blood pressure. But, according to Marcus, other effects may counteract this vascular narrowing.
Fine. But the question is about long-term impacts. I don’t see anything like an answer here. Will moderate caffeine intake increase, decrease, or have no impact on the risk of high blood pressure?
My take is that recent studies show no association, while others show slight protective effects, depending on a variety of factors such as individual caffeine metabolism.
If your blood pressure is too high and your caffeine intake is excessive, cutting back may be among the strategies suggested by your health care provider. That makes sense to me.
On the other hand, if you have high blood pressure but zero caffeine intake, I doubt that taking up caffeine would be wise. The benefits documented in the literature come from group data (you’re not a group) and they tend to be small. Other lifestyle changes and/or medication might be preferable, though one cardiologist quoted in The Wall Street Journal enthused that “We could even be recommending soon that people have coffee.” That strikes me as premature at best.
2. Impracticality.
Individuals metabolize caffeine differently depending on their genetics, their health, and their caffeine habits. (Witness my stepfather, who drank coffee all day and would pour himself a full cup around 10 p.m. to relax before bed. He reported sleeping well and never took naps. I’m still baffled.)
This kind of variation is one reason not to expect the AHA statement to specify exactly how much caffeine would be harmful or beneficial for you, the individual. No credible advice could ever be so granular.
At the same time, some guidance is possible, and I think the AHA statement fell short in that respect.
For one thing, the statement is framed as a report on caffeine, but most of the discussion concerns coffee, which contains additional compounds, such as polyphenols, that may benefit cardiovascular health.
In any case, the AHA claims that for most people, up to 3 to 5 cups of coffee per day is beneficial. This claim, they note, is based on the assumption that regular brewed coffee contains anywhere from 9.4 to 20 milligrams of caffeine per ounce.
Based on that assumption, an 8-ounce cup of brewed coffee would contain anywhere 75.2 to 160 milligrams. Multiply those figures by 3 versus 5 cups, respectively, and the range of values extends from 225.6 to 800 mg. That’s an enormous range!
We could assume, conservatively, that up to 225 mg of caffeine per day is safe and has cardiovascular benefits, or we could take AHA’s 400 mg figure at face value. Either way, most people will find it impossible to measure caffeine intake accurately. You can’t know for sure about the brewed coffee you buy or make at home. As for the products at your grocery store, I decided to visit a nearby Safeway yesterday to do some “research.” Here’s what I found:
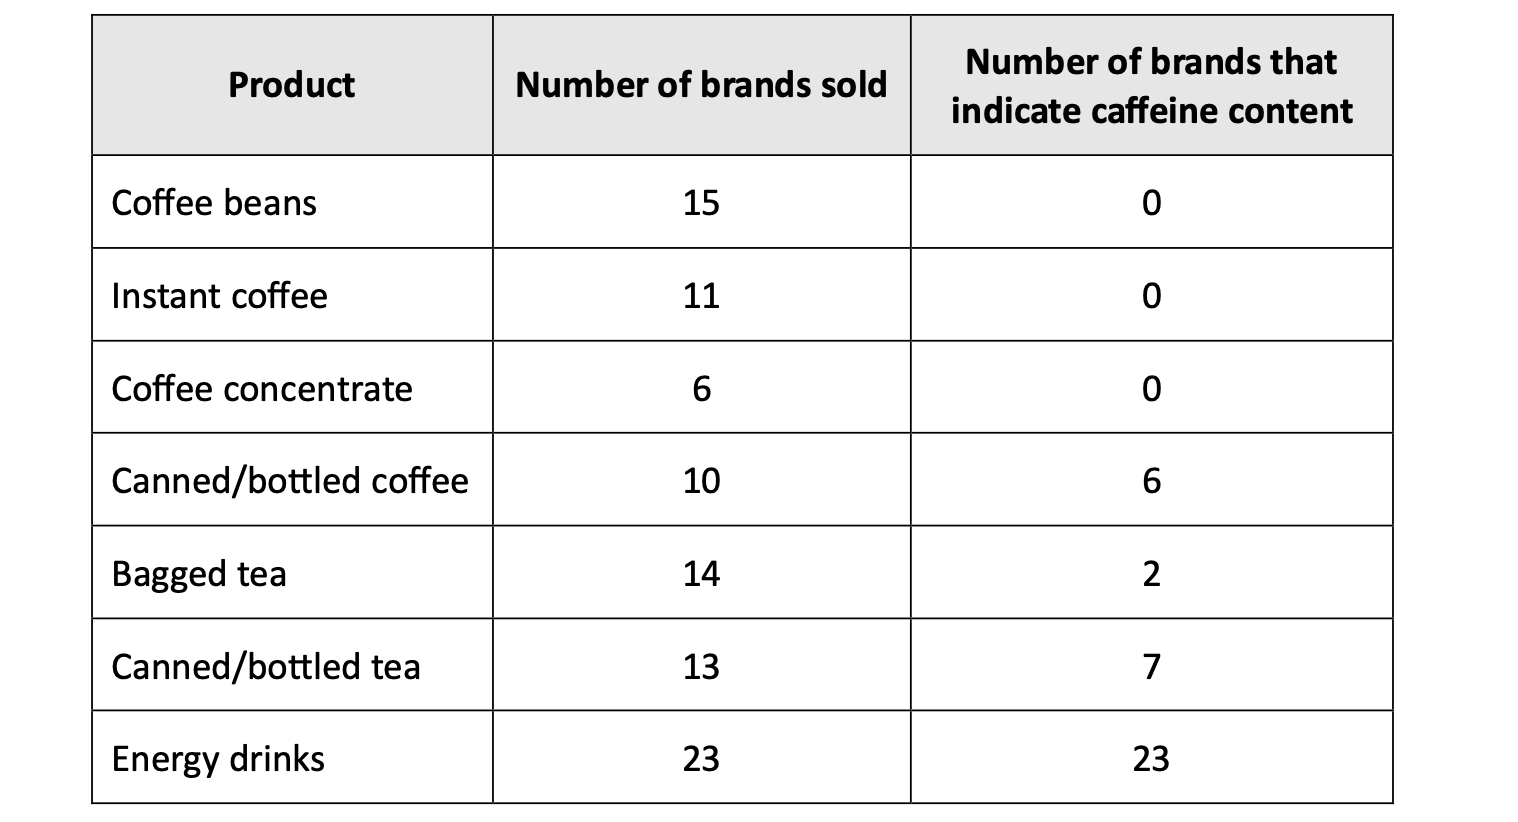
My takeaway is that with most products, you won’t know how much caffeine you’re consuming (though you can find data for some of the canned/bottled beverages on manufacturer websites).
I asked Dr. Marcus what he would advise consumers. His response was sensible, if not terribly informative:
“While I think it’s reasonable to trust that a given cup of coffee or tea can have an expected amount of caffeine, I would be wary of synthetic products that do not provide information on the amount of caffeine they contain...”
Fair enough. Be wary. I’ll circle back to this advice in a moment.
3. Bias.
I dislike energy drinks. In my darker moments I view their popularity as symptomatic of an overworked, attentionally-exhausted society clinging desperately to the remnants of its alertness.
Sorry, that was really dark. Mainly I just don’t like the way they taste. But I do feel slightly embarrassed to be on the verge of defending them.
The AHA statement reflects a strong and scientifically unjustified bias against energy drinks. Here’s most of what the statement says:
“Data on high doses of caffeine such as that found in energy drinks are limited and generally suggest cardiovascular harm.”
“[A]lthough data on energy drinks are limited, available studies generally suggest cardiovascular harm.”
“Consumption of energy drinks containing high concentrations of caffeine has been shown to result in significant increases in both systolic and diastolic blood pressures in healthy adults. In contrast, green coffee bean extract has been shown to decrease both systolic and diastolic blood pressures in adults...”
This is awful, and it smacks of the moralizing that Dr. Stein alluded to.
Sufficiently high doses of caffeine are harmful, regardless of whether they come from energy drinks or coffee or anything else.
Studies on energy drinks do not “generally suggest cardiovascular harm.” They suggest that high doses of caffeine are harmful, regardless of source.
And yes, high-caffeine energy beverages raise blood pressure temporarily. So does drinking anything that’s sufficiently caffeinated (Green coffee bean extract isn’t widely consumed and thus makes for an odd comparison here.)
In short, energy drinks are harmful only to the extent that their caffeine content is excessive. They may contain a lot of sugar, and other additives, but that’s a separate issue.
Is the caffeine content of energy drinks really too high?
Most people would say so, but I think the answer depends on your expectations. The two top-selling energy drinks in the U.S. – Red Bull and Monster – have roughly the same amount of caffeine per volume as brewed coffee.
Specifically, an 8-ounce can of Red Bull contains 80 mg of caffeine. That’s at the low end of what to expect from 8 ounces of regular coffee. A 16-ounce can of Monster contains 160 mg, the same amount per volume as Red Bull.
Meanwhile, my Safeway “study” found that every one of the 23 energy drinks sold there lists caffeine content on the product label.
In other words, energy drinks seem to be the only caffeine source on the market for which you can know, 100% of the time, exactly how much caffeine you’re consuming.
You might conclude that energy drinks are actually safer than other caffeine sources, at least in theory.
I added that “in theory” hedge for several reasons. Energy drinks contain lots of sweeteners and other additives. They’re marketed to young people who are more susceptible than adults to the harmful effects of caffeine. Consumers don’t necessarily read product labels. And there are some legitimately bad guys on the shelf. Brands like Hyde Xtreme, Bang Energy, C4 Ultimate and others have much more caffeine per volume than coffee does (Hyde Xtreme appears to lead the pack at 400 mg per 12-ounce can).
I gave Dr. Marcus a chance to redeem the AHA statement on energy drinks.
With respect to benefits, he noted that “it is important not to extrapolate any evidence of possible benefit [of caffeine] to other products, such as energy drinks.” I’m not sure why not. The caffeine you end up metabolizing from energy drinks is the same, chemically, as what you get from coffee.
As for safety, Dr. Marcus remarked that
“one of the properties generally inherent to energy drinks is that they tend to have much more concentrated forms of caffeine. A more sudden introduction of higher doses of caffeine may prohibit the usual self-titration that individuals otherwise may have the opportunity to do (relying on how they feel, such as whether they are starting to feel their heart race or feel jittery)...”
As I mentioned, the two top-sellers – regular Red Bull and Monster – are equivalent to the least caffeinated regular brewed coffee. Excessive caffeine doesn’t seem “generally inherent” to energy drinks. I’d only say that certain brands are concerning.
Again, expectations are critical. I hate to see 10-year-olds with Red Bulls, because one can would be equivalent to a cup of coffee. But most adults who have a Red Bull with lunch should be fine (apart from the 27 grams of added sugar).
AHA statement takeaway
I think the AHA statement is right in concluding that caffeine intake is associated with cardiovascular benefits. But it doesn’t follow that you should make any changes. You might be better off reflecting more broadly on your lifestyle, as opposed to micromanaging the number of coffees you drink.
Anthony Pearson, another cardiologist and brilliant Subtstacker I interviewed for this newsletter – this 2023 post of his is particularly relevant – explained some of the reasons why micromanaging caffeine intake might not be justified by the data:
“Because these studies are observational and come with all the limitations of nutritional epidemiology I think there is little value in parsing out the details. It is clear to me that depending on how the authors decide to do such analyses, what studies they choose to include, how vigorously the nutritional input data are collected, etc. the results will vary widely.”
Amen to that. I haven’t commented on the AHA’s claims about caffeine intake reducing risk of coronary heart disease, stroke, heart failure, atrial fibrillation, and diabetes, because the effects tend to be small but, as Dr. Pearson noted, could be smaller still (or larger) depending on how the data are treated. And, as always, confounds are possible. For instance, a 2011 meta-analysis that the AHA relied on heavily for conclusions about hypertension failed to control for variables like salt intake.
Public health messaging
Like in a game of telephone, the original data from studies on caffeine-cardiovascular associations have been transformed on their journey through meta-analyses, the AHA statement, news reports, and finally AI.
Most of the news coverage focuses narrowly on coffee counts. I’d blame the AHA for that, as their own press release is entitled: “Coffee and heart health: How many cups of caffeinated coffee are safe to drink each day?” Their estimate of “≈3–5 cups of coffee” is simplified to 5 in most reports, with some outlets focusing on safety and others on benefits:

The reportage is good but inconsistent, in the sense that not all sources mention key points raised in the statement.
For instance, ABC News notes that unfiltered coffees, including French press, espresso, and Turkish options, retain a compound called cafestol that can increase LDL (”bad”) cholesterol (though, as Dr. Stein told me, the effects are only clinically relevant at high levels of intake). The Wall Street Journal doesn’t mention anything about the filtered-unfiltered distinction.
However, unlike ABC, WSJ observes that the cardiovascular benefits of coffee drinks may be offset by excessive sugar, creamer, and other additives. Starbucks’ Frappuccinos contain more than 45 grams of added sugar – i.e., more than you’re supposed to consume in a day. This is “stealth dessert”, as Dr. Pearson calls it.
As for the AI chatbots I interacted with (ChatGPT and Claude), they both “read” the AHA statement, the AHA press release on the statement, and at least some of the high-circulation news media reports.
How well did they make sense of the content?
Both chatbots outperformed mainstream news outlets in summarizing the AHA statement as well as the broader literature.
This is not surprising, given that I could tailor questions to the AIs that they could then answer at length, geeking out on scientific details to the extent that I encouraged them. But one thing the chatbots couldn’t do well was to spot the limitations of the AHA statement.
In short, ChatGPT and Claude were better at summarizing content than evaluating it. Their evaluative work mostly consisted of offering platitudes (correlation does not prove causation) and citing findings from the literature that they viewed (sometimes incorrectly) as either consistent or inconsistent with the AHA statement.
There you go. A raison d’être for this 99.99% AI-free newsletter...
What AI is really good at includes things like reminding me how to spell “raison d’être” and assuring me that at least some readers would know what it means. (I asked.) You can’t get the latter from a dictionary.
What AI is not consistently good at, at least for the moment, is evaluating evidence-based claims such as the AHA statement. AI chatbots are better than you might think, but they need prompting, and guidance, and sometimes the evaluative work turns out badly anyway. In effect, they become Rube Goldberg machines, complicating tasks that are more easily accomplished by this particular human simply reading and reflecting on the research itself.
A final thought....
I believe that healthy living depends on listening to experts as well to your own body. Hopefully the messages are consistent. When they’re not, you have to make some hard choices.
For caffeine, I tend to prioritize what my body says. I drink one cup of coffee in the morning, occasionally a half-cup around noon, and I feel great – alert most of the day, no jitters, no heartburn, no difficulties falling asleep most nights. My health ain’t broke yet, so I’m not trying to fix it.
In short, I don’t think the prospect of slightly better cardiovascular health would compensate for jitters or impaired sleep or the other downsides of additional caffeine, even if my body eventually adjusted. Healthmaxxing all the time isn’t necessarily good for one’s health.
Thanks for reading!
Thank you, Ken, for this very helpful deep dive into the caffeine story.
I don't drink coffee or caffeinated commercial beverage, but will occasionally drink green tea. When my body needs to rest, I don't want to give it stimulants.
As a physician, I've seen patients with severe caffeine addiction. One was admitted to the psychiatric ward with hallucinations caused by consuming about 25 cups of coffee a day.
This is a nice review.
I appreciate the effort to try to tease out the specific purported benefits from specific formats and dosages/amounts of caffeine (based on that AHA statement). It’s really the basis of establishing the dose response relationship of any potential therapy.
I think you hit the most important points near the end. The problem with the guideline overall is that it is mostly based on observational data. There are very few RCT on caffeine (the Crave trial and Decaf trial being notable exceptions). To me it is a fatal flaw (and a novice level one at that) for the AHA to try to offer “scientific” guidance based on such low quality evidence. They pretend to know something (and with authoritative bona fides) when they don’t (and can’t, based on the level of evidence).