


In the ideal world we’re all healthy, food and exercise are the only medicines, and “Big Pharma” would be the name of a pro wrestler.
In the real world, most of us use medication to maintain or improve our health.
For more than two decades, the percentage of Americans who’ve taken at least one prescription drug in the past 30 days has stayed remarkably stable. This was 46.7% of us in 2001–2004, compared to 46.8% from 2017 through March 2020.
During the same time period, the use of multiple prescription drugs increased among some groups. For instance, the percentage of adults 65 and older who take 5 or more drugs rose from 33% to 43%.

Why are older people increasingly reliant on multiple medicines?
A little of this, a little of that. We’re living longer. Obesity, type 2 diabetes, and related conditions are more prevalent. Diagnostic technologies are improving. And combination therapy – prescribing multiple drugs for the same condition – has become more common.
Ideally, healthy living is the best medicine, and you only take the prescription drugs you need. Maybe it’s one drug, maybe many, but assuming no unwanted effects, the exact number per se shouldn’t mean much, right? As noted in a 2024 review,
“...it is not possible to account for clinical appropriateness through simple medication counts.”
You can probably guess what’s coming next.
Last week I encountered a new study that questions this conclusion. The data suggests that beyond a certain point, the more medications people take, the shorter they tend to live.
In other words, the number of prescriptions you routinely fill may be informative in and of itself.
When I first heard about this study, I thought: Ho-hum. Anyone could’ve guessed as much. This is just how probabilities work. Since any one medication is potentially harmful, the more of them you take, the greater the chances of adverse effects, drug interactions, and injuries resulting from influences on cognition, balance, and/or coordination.
Then I looked at the actual study. My initial impression was totally off base. The researchers found that even after taking into account the kinds of factors I just described, the sheer number of medications is associated with mortality risk.
Should we be counting our prescription drugs? Should some of us be talking with our health care providers about scaling back?
Whether or not we should, it’s probably already happening. The study has been covered by high-circulation outlets such as Fox News and Medscape (not to mention some number of blogs and social media posts).
This is a strong study – I found the data persuasive – but the conclusion is more nuanced than just count your meds. (Fox News, as you’ll see, mishandled some of those nuances.) So, once I‘ve laid out the main findings, I'll sort through some of the takeaways.
A quick semantic note before digging in.
Polypharmacy
“Polypharmacy” is the term experts use for taking numerous prescription drugs simultaneously. As the lead author of the new study, Dr. Alexander Chaitoff, noted in an email to me this week
“”5 [or more] medications is the most common way to define polypharmacy”
He also added some qualifications I’ll get into later. Importantly, 5 is not a wholly arbitrary number. Rather, depending on the outcome, it’s the point at which some studies show health risks beginning to increase. The possibility that the number itself is important is explored especially meticulously in the new study.

Polypharmacy and mortality
This study, led by Dr. Chaitoff and colleagues at University of Michigan, University of Bern, and Harvard, was published in the Journal of the American Geriatrics Society on July 8th.
The first thing I noticed about the writeup is that, through no fault of the authors, there’s a lot of encouragement not to read it.
The online version contains an abstract, a graphical abstract, a summary, a discussion, and an unsolicited invitation from AI Companion. (Of course, you can also upload the article to free versions of ChatGPT or Claude and ask questions there too.)
I’m old-fashioned: I read the study. (I imagine some tech bro thinking: Chump. But I can assure you – as I discover week after week – that human eyes are still needed on the fine print.)
Chaitoff and colleagues looked at 7,828 individuals ages 65 and older who participated in the National Health and Nutrition Examination Survey (NHANES) from 1999 to 2016. Participants were followed for an average of 8.5 years.
Based on data obtained by NHANES staff, each participant was identified as having up to three of the following high-risk medication uses:
Polypharmacy
Drug-drug interactions (DDIs)
Potentially inappropriate medication uses (PIMs).
Polypharmacy was defined as 5 or more prescription medications. DDIs consisted of drug combinations known to multiply the risk of adverse events. PIMs were drugs representing one of 16 categories deemed risky for older adults.
Elephas expulsus
Before getting to the data, I want to quickly shoo away an elephant in the room.
We’d expect greater medication use to be linked to poorer health and greater mortality risk. Not because medicines undermine health, but because less healthy people tend to take more medicines.
This illustrates a reverse causality problem that Chaitoff and colleagues did a nice job of addressing. They did so by controlling for a variety of demographic variables as well as health status, comorbidities, health behaviors, and baseline organ functioning. (See my Appendix for details.)
Put simply, even though sicker people may tend to take more medicines, the researchers established a link between polypharmacy and mortality even after taking into account the effects of baseline health.
Two key findings
1. Polypharmacy was associated with higher mortality risk.
The figure below shows that during followup, participants who used 5 or more prescription drugs (orange line) were less likely to have survived than participants taking a fewer number (gray line). Overall, polypharmacy increased mortality risk by 38% during this time period.
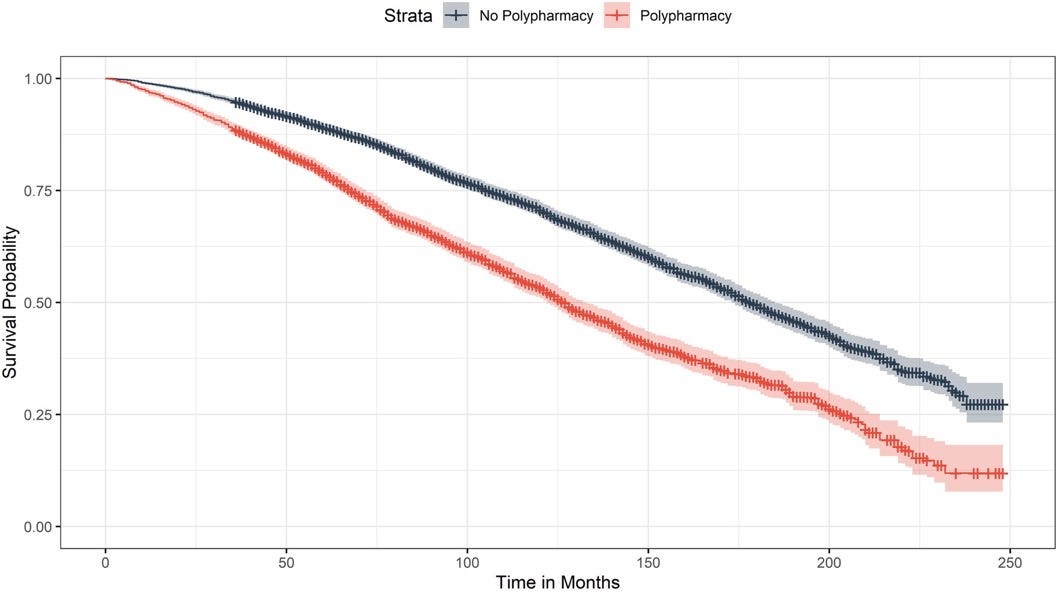
This finding is consistent with prior evidence, but keep in mind that some folks in the polypharmacy group were taking drugs in the DDI and/or PIM categories. Perhaps what led to their earlier demise wasn’t the quantity but rather the types of drugs they were taking.
Drum roll please...
2a. Drug-drug interactions (DDIs) and potentially inappropriate medications (PIMs) were not associated with higher mortality risk, after controlling for polypharmacy.
2b. Polypharmacy was associated with higher mortality risk, after controlling for DDIs and PIMs.
These findings are remarkable. They suggest that taking 5 or more prescription drugs can be harmful, but not because of drug interactions, use of inappropriate medications, or existing health conditions. Something about the number of drugs per se may have an effect on our bodies.
What the results tell us
Why would taking more prescription drugs increase mortality risk? Chaitoff and colleagues speculate that
“polypharmacy may act as a chronic physiologic stressor, depleting homeostatic reserves over time”
There’s some empirical support for this hypothesis, but for the moment it’s speculative and, with respect to mechanism, seems a little hazy.
No matter. The results tell us something important about medication use, though the takeaway is not to simply count drugs. Rather, as Chaitoff and colleagues put it,
“...clinicians should remain vigilant regarding specific medication quality, [but] the total number of medications may be the important clinical data point for identifying older adults at the highest risk for adverse outcomes.”
In other words, counting drugs is a good way to get one piece of information relevant to decisions about prescription lists. It’s just a datapoint, along with so many others we should be considering. At the same time, as Dr. Chaitoff told me, medication counts need to be viewed flexibly, since, for instance,
“the risk difference at 4 versus 5 medications isn’t necessarily as drastically different as some may assume given how much we use the 5 cutoff”
He also pointed me to evidence suggesting that outcomes matter. Fewer than 5 medications may increase the risk of cognitive impairment, for example, while the cut-off for frailty may be more than 5. Given that increases in risk with each additional medication are small, comprehensive discussion of risks and benefits is always advisable.
Public health messaging
I want to pick on Fox News for a moment. But, I want to assure you that I’ve got no political axe to grind here. Liberal outlets like CNN and even The New York Times sometimes fall short in their science journalism. I’m singling out Fox because it’s the highest-circulation outlet to cover the study, and one shortcoming of its reportage illustrates how easily research findings can be misconstrued.

Even before reading the article, you can spot the problem. Following that big, boldfaced headline linking polypharmacy to a “higher risk of death”, the subheadline notes that “More than half of participants experienced at least one high-risk medication pattern.”
This is misleading, because two of those patterns (DDIs and PIMs) weren’t associated with greater risk in this particular study. That’s one of the most important messages from the data, and it sets this study apart from those that came before.
Any confusion may be reinforced by the article itself, where potentially millions of readers would see the following:
“More than half of participants (54.3%) fell into at least one high-risk medication category. The largest group consisted of older adults taking five or more prescription drugs (polypharmacy).
Another group, 37.6% of those studied, used medications deemed risky for older individuals, such as drugs that can increase the risk of confusion or falls, the study revealed.
Additionally, 11.4% took combinations of medications that are known to cause major drug-to-drug interactions.
“People taking more medications often have more underlying health conditions, which may also contribute to their higher mortality risk,” Katy Dubinsky, New York-based pharmacist and founder of PostGigs, who was not involved in the study, told Fox News Digital.”
All three medication risk factors are identified here, without noting that the researchers teased out the influences of each and only found effects for polypharmacy.
(I suppose it’s cool that Fox invited a pharmacist to comment on the study, but her comment fails to acknowledge that the researchers took into account the very concern that she raised. As I mentioned, they did control for underlying health conditions, plus a whole lot more.)
How should we think about prescription medicine use?
One concern I have about studies like this is that they may inadvertently fuel a society-wide tendency to fixate on quantitative health targets. 10,000 steps per day, 8 glasses of water – that sort of thing. Not that these are unhealthy goals, but that their specificity is simply not justified by the data. We shouldn’t necessarily stress about falling short, any more than meeting these targets guarantees healthy living. My father easily drank 10 glasses of water per day. He was also a chain-smoker and an alcoholic.
My point is that whether you’re a health care provider, a patient, or an AI chatbot, there may be a temptation (if AI can be said to be “tempted”) to treat 5 medications as a simple cut-off, below which there’s no cause for concern and above which intervention is needed.
I raised this concern with Dr. Chaitoff. His response emphasized the need for broad strategizing around prescription medication use:
“In the short term, I think patients and clinicians should regularly review entire medication regimens to make sure everybody agrees there is still benefit to each one. Our paper, and others that came before it, might suggest it is especially important for this practice to happen for people on 5+ medications, but one could argue it should be a regular practice for all patients using prescription medications...”
I agree, and as Chaitoff and colleagues suggest in their article, medication counts should be treated as one datapoint among many in determining the best approach to patient care.
Finally, given the extent to which public health is so deeply politicized, I asked Dr. Chaitoff the following:
“Are you concerned that your findings could be misread as a sort of condemnation of prescription drugs? (I can imagine both political ideologues and social media influencers, for different reasons, engaging in this kind of misreading.)”
His reply was modest and insightful, if a bit pessimistic in places:
“I hope that readers see what we set out to do, recognize the value of that skeptical mindset and the incremental value of this study within the much broader literature, and use this work to design the next study, which will ultimately be better.
More broadly, I do think this is why it’s important for authors to be honest about the limitations of their studies, and for others – clinicians, reporters, etc. – to read those limitations so that measured commentaries can be provided. That said, regardless of the reported limitations, I think most individuals see what they want to see in most studies, except in rare cases. This isn’t necessarily a bad thing – we are Bayesian thinkers, and it is reasonable that only a very strong piece of evidence should substantially move a well-researched prior. In the era of evidence-based medicine, medical practice changes only with an accumulation of evidence...I do not think this study will convince an individual who believes everyone needs more medication that there could be risks, and I do not think it will convince an individual who views prescription medications poorly that the evidence is only associative. Ultimately, one paper won’t settle a polarized debate, but if it helps inform and frame the next study, it has done its job.
I think this study has done a fine job. Yes, there’s a possibility of residual confounding and other limitations that the authors acknowledge, but I am persuaded that the data call for a closer look at the possibility that taking multiple medications creates physiological stress not attributable to the effects of any individual drug or drug interaction.
Final thoughts
Like many people, I have mixed feelings about prescription drugs. They’re a blessing when you need them, especially as you get older, but it’s troubling to see them overprescribed in some cases and/or used to treat the effects of unhealthy living. Most of the 10 most commonly prescribed drugs in the U.S. treat hypertension, high cholesterol, type 2 diabetes and other problems that, depending on the person, may be caused to some extent or exacerbated by lifestyle.
The new study highlights some of the many complexities around decisions to take medication. There’s so much uncertainty baked into the process. You never know, down to the millimeter, how much a condition like hypertension is driven by your genetics, which you can’t control, versus potentially modifiable factors like diet, exercise, stress, and sleep. The takeaway is simply that as you weigh the risks of any drug against its potential benefits, the total number of medications you take may deserve a place in your calculations too.
Thanks for reading!
Appendix: Statistical note
Polypharmacy, DDIs, and PIMs overlap somewhat, though multicollinearity was not a major issue in the researchers’ final Cox regression model (VIF < 3).
This model included the three medication risk factors and adjusted for sociodemographic characteristics (age, sex, race/ethnicity, etc.), comorbidities/health conditions (cardiovascular disease, heart failure, COPD, liver disease, non-skin cancer, anemia), baseline organ function (blood pressure, BMI, AST and ALT liver enzymes, glomerular filtration rate, HbA1c), and health behaviors (smoking and alcohol intake).
In this model, polypharmacy was significantly associated with mortality (HR = 1.38), but each of the other two risk factors (DDIs and PMIs) was not.
Oh, man, Ken, I was made for this post!
I was asked to see a patient in our out-patient clinic - a 65+ year old woman with an unspecified psychotic disorder, who was increasingly disruptive in the Psychotic Disorder therapy group, so I scheduled her an initial appointment. When I reviewed her chart prior to seeing her, she was taking thirteen separate psych meds, or meds for side-effects related to the psych meds, by 5 separate providers, either by residents long gone, or by psychiatrists from the county hospital from which she had transferred from to our clinic. We managed to continue to refill all thirteen, unabated, no questions asked. I decided to see her first, assess the situation, and see if some of the meds could be stopped. She was pleasant enough; she did not like the co-facilitator of the group (thus the "disruptive behaviour); she had no idea of the purpose of the meds; and she agreed to meet with me, once a week, for two months. Surprisingly, our sessions went marvelously. Her mood and affect rapidly improved; her social skills improved in the group, and even outside the group; she slept better; she improved her diet; she returned to walking, etc. etc. The psychologist, at week six, came to me and said he was genuinely very pleased with her improvement since she began seeing me. Then, at week seven, one of the nurses came to me and said, "The pharmacy called and told me to tell you that your patient did not refill any of her medications two weeks prior to beginning her sessions with you." Beers Criteria be damned, I burst out laughing. The next day when she came for her appointment, she asked why I was smiling, I told her I knew she had stopped her meds. She told me the delivery service could not find her new apartment, and she didn't bother to call them back. Was I disappointed? Certainly not. For her own safety, I'd wished she had told me, but whatever... Will she live longer? Heaven knows, but when I left, she certainly seemed a great deal happier, which was the payoff we were looking for, no?
This was a great read, and you highlighted the part most coverage skips: the 38% signal held even after they adjusted for drug-drug interactions and potentially inappropriate meds. That is the uncomfortable finding.
If the risk does not reduce to a few bad actors, then the count itself is doing something, which fits their homeostatic reserve framing better than a hunt for the single wrong pill. It quietly shifts deprescribing from spotting the offender to lowering total burden.